

About EoE
EVEN IF YOUR PATIENTS SAY THEY ARE FINE, EoE IS A CHRONIC, PROGRESSIVE TYPE 2 INFLAMMATORY DISEASE
EoE requires lifelong follow-up to ensure treatment adherence and efficacy, limit long-term complications, and reduce need for dilations1-3
DISABLING SYMPTOMS
Adult and adolescent patients with EoE experience1,4-6:
- Dysphagia
- Noncardiac chest pain
- Food impaction and subsequent bolus removal
- Regurgitation
TREATMENT DELAYS
- 6 YEARS median diagnostic delay from symptom onset7
- ≤2 YEARS of diagnostic delay; 88% of patients experienced inflammation-driven changes and/or increased fibrosis7
- 8% increased risk of fibrostenosis every year7
- 26% increased risk in stricture for each year of gap in treatment8
- Gap in care: Only ~1 in 5 patients undergo biopsy at the time of EFI (47% of those biopsied are diagnosed with EoE)9
UNDERLYING INFLAMMATION
~75% of EoE patients have at least one coexisting atopic type 2 inflammatory disease3,10:
- Allergic rhinitis
- Asthma
- Atopic dermatitis
- Food allergies
EFI, esophageal food impaction; EoE, eosinophilic esophagitis.
LIVING WITH EoE PLACES A HIGH BURDEN ON BOTH ADULTS AND ADOLESCENTS
High EoE-associated emotional and psychological burden and perceived stigma contribute to a poor HRQoL11,a


a Web survey in adolescents (n=211; caregiver-reported) and adults (n=184).
HRQoL, health-related quality of life.
References:
- Mukkada V, Falk GW, Eichinger CS, King D, Todorova L, Shaheen NJ. Health-related quality of life and costs associated with eosinophilic esophagitis: a systematic review. Clin Gastroenterol Hepatol. 2018;16(4): 495-503.e8.doi:10.1016/j.cgh.2017.06.036
- Chehade M, Jones SM, Pesek RD, et al. Phenotypic characterization of eosinophilic esophagitis in a large multicenter patient population from the Consortium for Food Allergy Research. J Allergy Clin Immunol Pract. 2018;6(5):1534-1544.e5. doi:10.1016/j.jaip.2018.05.038
- Gandhi NA, Bennett BL, Graham NMH, Pirozzi G, Stahl N, Yancopoulos GD. Targeting key proximal drivers of type 2 inflammation in disease. Nat Rev Drug Discov. 2016;15(1)35-50. doi:10.1038/nrd4624
- D'Allessandro A, Esposito D, Pesce M, Cuomo R, De Palma GD, Sarnelli G. Eosinophilic esophagitis: from pathophysiology to treatment. World J Gastrointest Pathophysiol. 2015;6(4):150-158. doi:10.4291/wjgp.v6.i4.150
- Li-Kim-Moy JP, Tobias V, Day AS, Leach S, Lemberg DA. Esophageal subepithelial fibrosis and hyalinization are features of eosinophilic esophagitis. J Pediatr Gastroenterol Nutr. 2011;52(2):147-153: doi:10.1097/MPG.0b013e3181ef37a1
- Straumann A, Bussmann C, Zuber M, Vannini S, Simon HU. Eosinophilic esophagitis: analysis of food impaction and perforation in 251 adolescent and adult patients. Clin Gastroenterol Hepatol. 2008;6(5):598-600. doi:10.1016/j.cgh.2008.02.003
- Schoepfer AM, Safroneeva E, Bussman C, et al. Delay in diagnosis of eosinophilic esophagitis increases risk for stricture formation in time-dependent manner. Gastroenterology. 2013;145(6):1230-6.e1-2 doi:10.1053/j.gastro.2013.08.015
- Chang NC, Thakkar KP, Ketchem CJ, Eluri S, Reed CC, Dellon ES. A gap in care leads to progression of fibrosis in eosinophilic esophagitis patients. Clin Gastroenterol Hepatol. 2022;20(8):1701-1708.e8. doi:10.106/j.cgh.2021.10.028
- Redd WD, Dellon ES, Bekal P, et al. Real-world study of biopsy practices during food impactions in the emergency department: multi-state GI practice. Presented at: 2025 American College of Gastroenterology (ACG) Annual Meeting: Phoenix, AZ, USA; October 24-29, J Clin Gastroenterol. 2017;51(8):659-668. doi:10.1097/mcg.00000000000000879
- van Rhijn BD, Bredenoord AJ. Management of eosinophilic esophagitis based on pathophysiological evidence. J Clin Gastroenterol. 2017;51(8):659-668. doi:10.1097/MCG.0000000000000879
- Gold BD, Goodwin B, Davis K, et al. Health-related quality of life and perceived stigma in eosinophilic esophagitis: a real-world, US, web-based survey. Gastro Hep Adv. 2024;3:1087-1097. doi:1016/j.gastha.2024.07.0
EoE IS A CHRONIC, PROGRESSIVE TYPE 2 INFLAMMATORY DISEASE AFFECTING PATIENTS AS YOUNG AS 1 YEAR OLD
EoE requires lifelong follow-up to ensure treatment adherence and efficacy, limit long-term complications, and reduce the need for esophageal dilations1-3
DISABLING DISEASE BURDEN
Children with EoE experience1:
- Abdominal pain and vomiting
- Weight loss, impaired growth, and failure to thrive
- Adaptive behaviors to deny or mask symptoms
- Coexisting atopic type 2 inflammatory diseases
URGENCY FOR EARLY DIAGNOSIS
- Delay in diagnosing and treating EoE can impact childhood growth2
- Early diagnosis improves HRQoL and may slow disease progression1
- Patients achieving histologic remission experienced 77% reduction in stricture development3
|
CHILDREN AND CAREGIVERS NEED A THERAPY THAT TREATS THE UNDERLYING
|
EoE, eosinophilic esophagitis; HRQoL, health-related quality of life.
References:
- Muir AB, Brown-Whitehorn T, Godwin B, Cianferoni A. Eosinophilic esophagitis: early diagnosis is the key. Clin Exp Gastroenterol. 2019;12:391-399. doi:10.2147/CEG.S175061
- Chehade M, Hiremath GS, Zevit N, et al. Disease burden and spectrum of symptoms that impact quality of life in pediatric patients with eosinophilic esophagitis. Gastro Hep Adv. 2024;3(8):1054-1068. doi:10.106/j.gastha.2024.08.009
- Strauss Starling A, Ren Y, Li H, et al. Reducing eosinophil counts in eosinophilic esophagitis in children is associated with reduction in later stricture development. Am J Gastroenterol. 2024;119(10):2002-2009. doi:10.14309/ajg.0000000000000002830
EVEN IF YOUR PATIENTS SAY THEY ARE FINE, EoE IS A CHRONIC, PROGRESSIVE TYPE 2 INFLAMMATORY DISEASE
EoE requires lifelong follow-up to ensure treatment adherence and efficacy, limit long-term complications, and reduce need for dilations1-3
DISABLING SYMPTOMS
Adult and adolescent patients with EoE experience1,4-6:
- Dysphagia
- Noncardiac chest pain
- Food impaction and subsequent bolus removal
- Regurgitation
TREATMENT DELAYS
- 6 YEARS median diagnostic delay from symptom onset7
- ≤2 YEARS of diagnostic delay; 88% of patients experienced inflammation-driven changes and/or increased fibrosis7
- 8% increased risk of fibrostenosis every year7
- 26% increased risk in stricture for each year of gap in treatment8
- Gap in care: Only ~1 in 5 patients undergo biopsy at the time of EFI (47% of those biopsied are diagnosed with EoE)9
UNDERLYING INFLAMMATION
~75% of EoE patients have at least one coexisting atopic type 2 inflammatory disease3,10:
- Allergic rhinitis
- Asthma
- Atopic dermatitis
- Food allergies
EFI, esophageal food impaction; EoE, eosinophilic esophagitis.
LIVING WITH EoE PLACES A HIGH BURDEN ON BOTH ADULTS AND ADOLESCENTS
High EoE-associated emotional and psychological burden and perceived stigma contribute to a poor HRQoL11,a
a Web survey in adolescents (n=211; caregiver-reported) and adults (n=184).
HRQoL, health-related quality of life.
References:
- Mukkada V, Falk GW, Eichinger CS, King D, Todorova L, Shaheen NJ. Health-related quality of life and costs associated with eosinophilic esophagitis: a systematic review. Clin Gastroenterol Hepatol. 2018;16(4): 495-503.e8.doi:10.1016/j.cgh.2017.06.036
- Chehade M, Jones SM, Pesek RD, et al. Phenotypic characterization of eosinophilic esophagitis in a large multicenter patient population from the Consortium for Food Allergy Research. J Allergy Clin Immunol Pract. 2018;6(5):1534-1544.e5. doi:10.1016/j.jaip.2018.05.038
- Gandhi NA, Bennett BL, Graham NMH, Pirozzi G, Stahl N, Yancopoulos GD. Targeting key proximal drivers of type 2 inflammation in disease. Nat Rev Drug Discov. 2016;15(1)35-50. doi:10.1038/nrd4624
- D'Allessandro A, Esposito D, Pesce M, Cuomo R, De Palma GD, Sarnelli G. Eosinophilic esophagitis: from pathophysiology to treatment. World J Gastrointest Pathophysiol. 2015;6(4):150-158. doi:10.4291/wjgp.v6.i4.150
- Li-Kim-Moy JP, Tobias V, Day AS, Leach S, Lemberg DA. Esophageal subepithelial fibrosis and hyalinization are features of eosinophilic esophagitis. J Pediatr Gastroenterol Nutr. 2011;52(2):147-153: doi:10.1097/MPG.0b013e3181ef37a1
- Straumann A, Bussmann C, Zuber M, Vannini S, Simon HU. Eosinophilic esophagitis: analysis of food impaction and perforation in 251 adolescent and adult patients. Clin Gastroenterol Hepatol. 2008;6(5):598-600. doi:10.1016/j.cgh.2008.02.003
- Schoepfer AM, Safroneeva E, Bussman C, et al. Delay in diagnosis of eosinophilic esophagitis increases risk for stricture formation in time-dependent manner. Gastroenterology. 2013;145(6):1230-6.e1-2 doi:10.1053/j.gastro.2013.08.015
- Chang NC, Thakkar KP, Ketchem CJ, Eluri S, Reed CC, Dellon ES. A gap in care leads to progression of fibrosis in eosinophilic esophagitis patients. Clin Gastroenterol Hepatol. 2022;20(8):1701-1708.e8. doi:10.106/j.cgh.2021.10.028
- Redd WD, Dellon ES, Bekal P, et al. Real-world study of biopsy practices during food impactions in the emergency department: multi-state GI practice. Presented at: 2025 American College of Gastroenterology (ACG) Annual Meeting: Phoenix, AZ, USA; October 24-29, J Clin Gastroenterol. 2017;51(8):659-668. doi:10.1097/mcg.00000000000000879
- van Rhijn BD, Bredenoord AJ. Management of eosinophilic esophagitis based on pathophysiological evidence. J Clin Gastroenterol. 2017;51(8):659-668. doi:10.1097/MCG.0000000000000879
- Gold BD, Goodwin B, Davis K, et al. Health-related quality of life and perceived stigma in eosinophilic esophagitis: a real-world, US, web-based survey. Gastro Hep Adv. 2024;3:1087-1097. doi:1016/j.gastha.2024.07.0
EoE IS A CHRONIC, PROGRESSIVE TYPE 2 INFLAMMATORY DISEASE AFFECTING PATIENTS AS YOUNG AS 1 YEAR OLD
EoE requires lifelong follow-up to ensure treatment adherence and efficacy, limit long-term complications, and reduce the need for esophageal dilations1-3
DISABLING DISEASE BURDEN
Children with EoE experience1:
- Abdominal pain and vomiting
- Weight loss, impaired growth, and failure to thrive
- Adaptive behaviors to deny or mask symptoms
- Coexisting atopic type 2 inflammatory diseases
URGENCY FOR EARLY DIAGNOSIS
- Delay in diagnosing and treating EoE can impact childhood growth2
- Early diagnosis improves HRQoL and may slow disease progression1
- Patients achieving histologic remission experienced 77% reduction in stricture development3
|
CHILDREN AND CAREGIVERS NEED A THERAPY THAT TREATS THE UNDERLYING
|
EoE, eosinophilic esophagitis; HRQoL, health-related quality of life.
References:
- Muir AB, Brown-Whitehorn T, Godwin B, Cianferoni A. Eosinophilic esophagitis: early diagnosis is the key. Clin Exp Gastroenterol. 2019;12:391-399. doi:10.2147/CEG.S175061
- Chehade M, Hiremath GS, Zevit N, et al. Disease burden and spectrum of symptoms that impact quality of life in pediatric patients with eosinophilic esophagitis. Gastro Hep Adv. 2024;3(8):1054-1068. doi:10.106/j.gastha.2024.08.009
- Strauss Starling A, Ren Y, Li H, et al. Reducing eosinophil counts in eosinophilic esophagitis in children is associated with reduction in later stricture development. Am J Gastroenterol. 2024;119(10):2002-2009. doi:10.14309/ajg.0000000000000002830
Progression
UNCONTROLLED EoE LEADS TO LONG-TERM DAMAGE, LEAVING ADULTS AND ADOLESCENTS AT RISK, EVEN IF THEY SAY THEY ARE FINE
Assess treatment adherence and efficacy regularly to ensure esophageal healing and inactive EoE, reducing long-term complications and the need for future dilations1
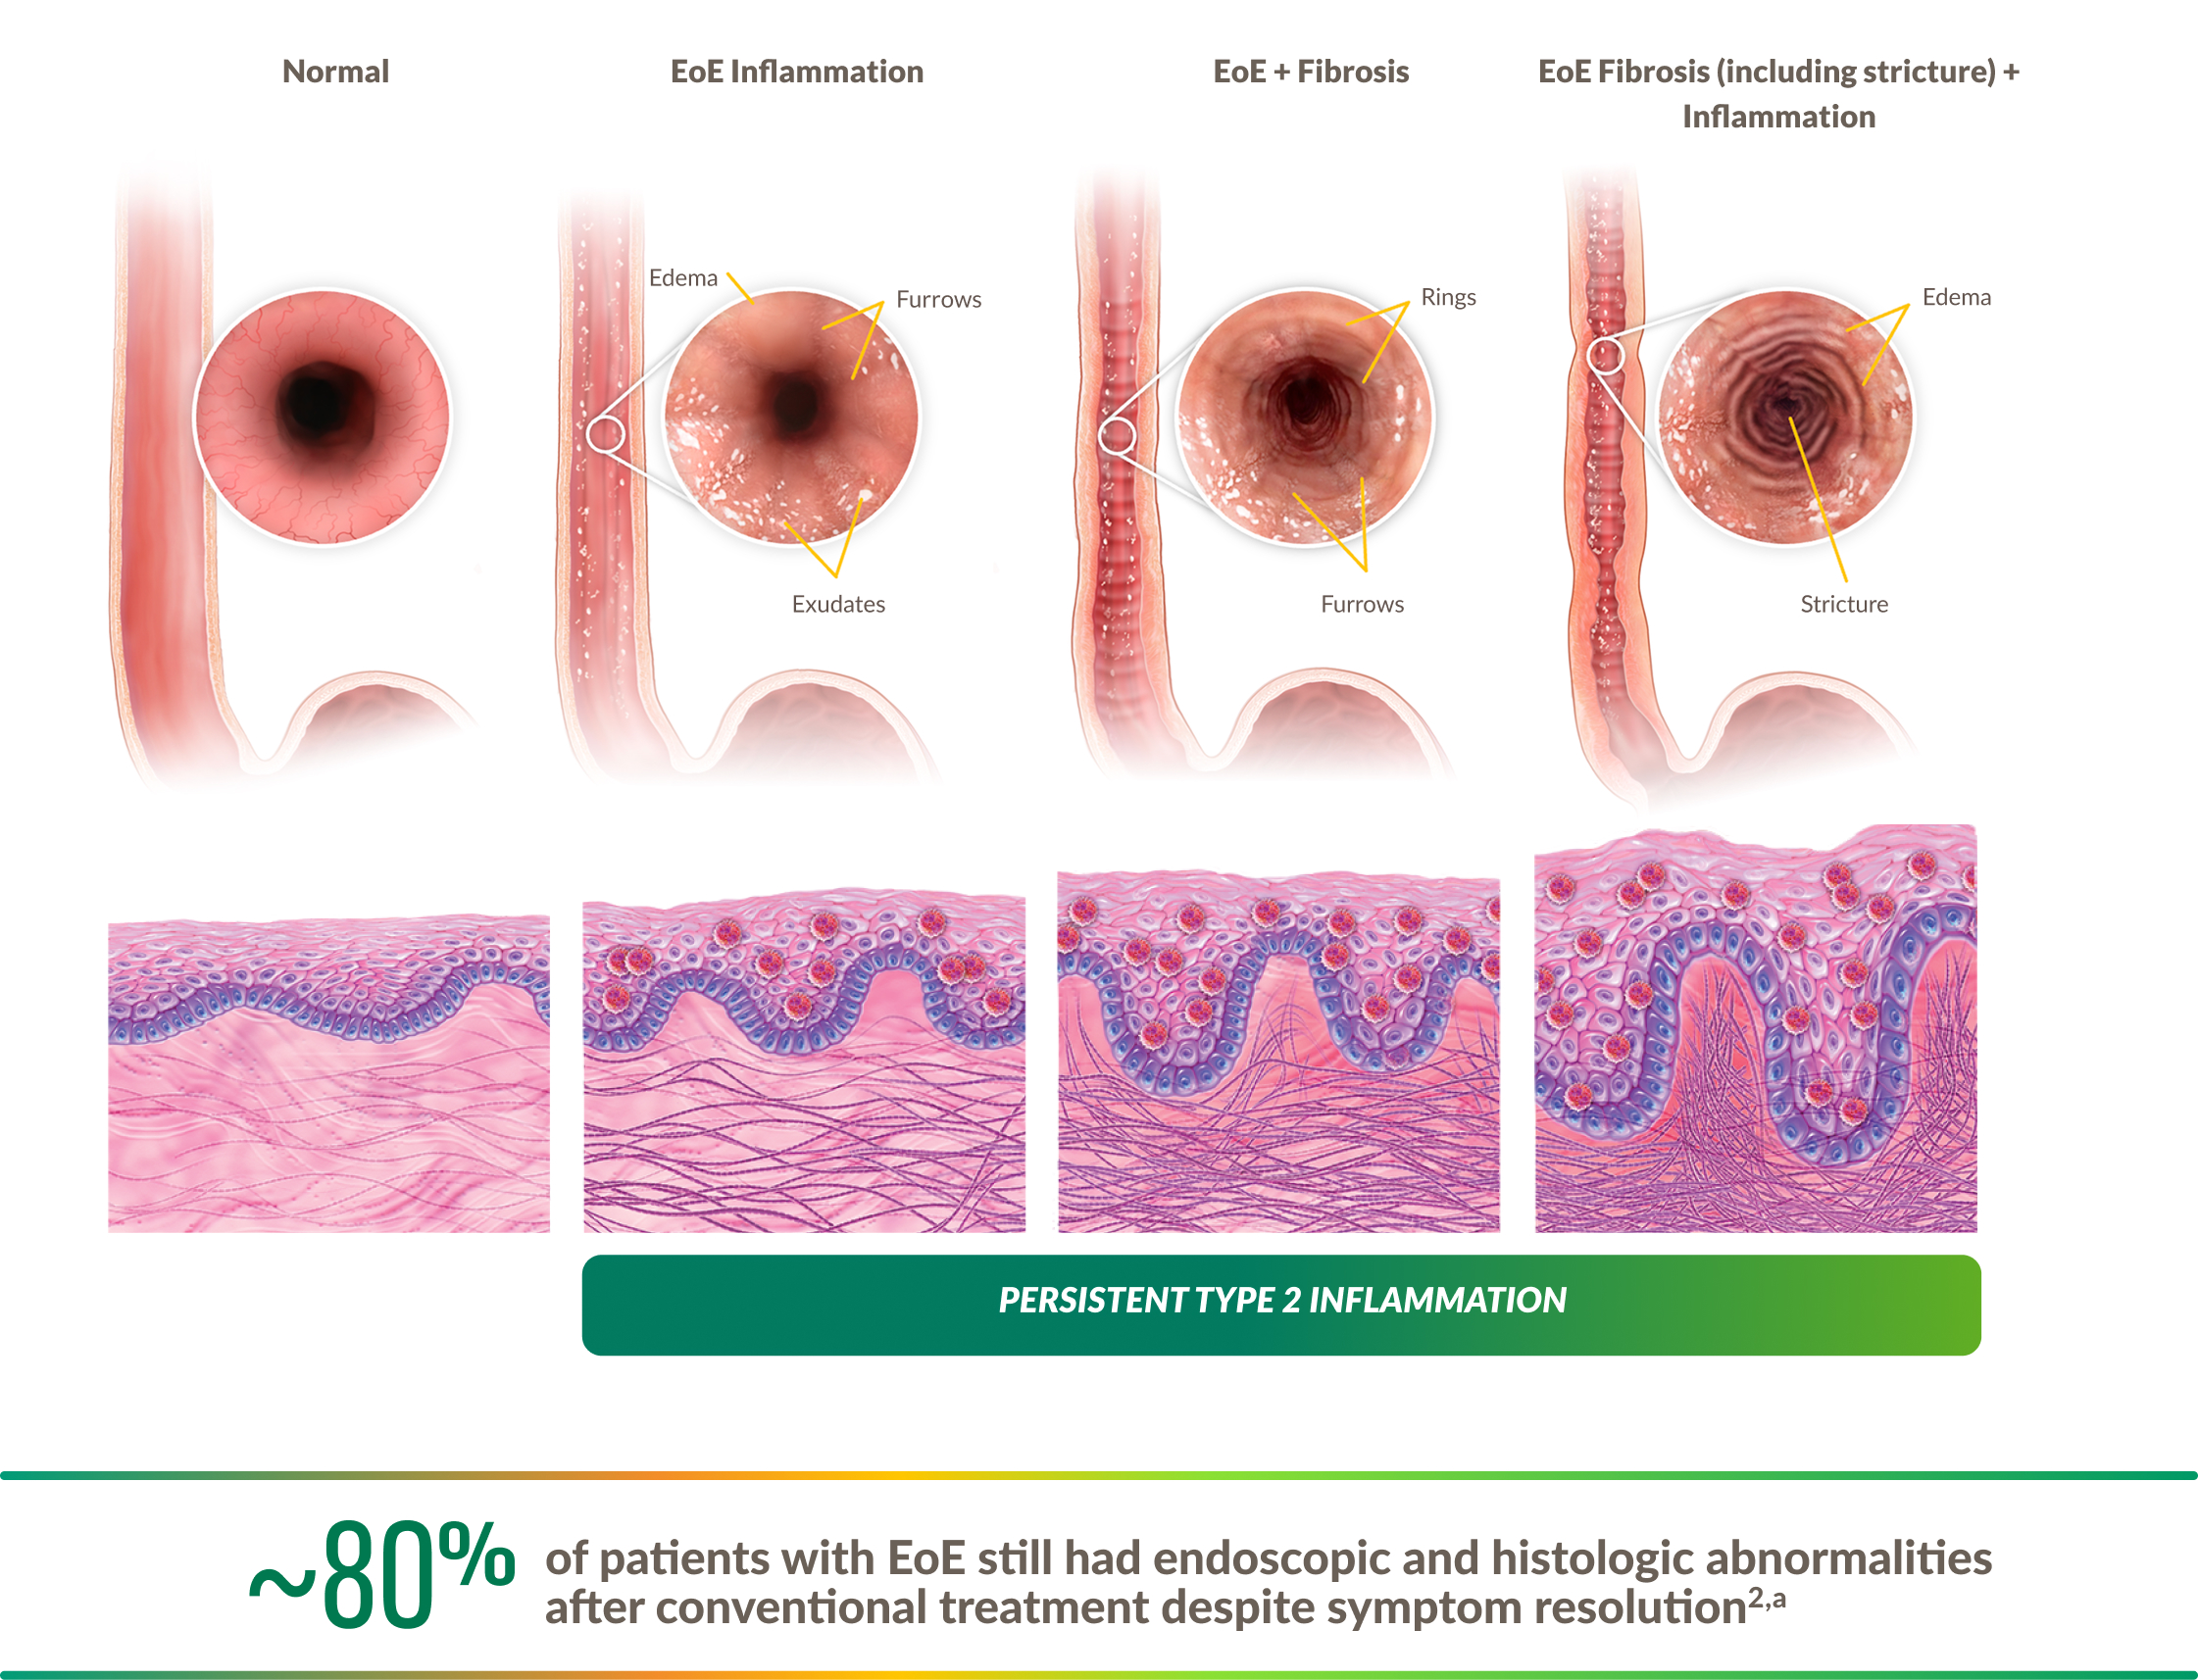

a Multicenter study in 269 patients aged ≥17 years.
b Retrospective study in 200 adult patients, responders to TCS.
EoE, eosinophilic esophagitis; TCS, topical corticosteroids.
References:
- Saravino EV, Fassan M, de Bortoli N, et al. Italian EoExpert panel recommendation for disease control, switching criteria, and follow-up in eosinophilic esophagitis from pediatric to adult age. Ther Adv Gastroenterol. 2025;18:17562848251337515. doi:10.1177/17562848251337515
- Safroneeva E, Straumann A, Schoepfer AM. Latest insights on the relationship between symptoms and biologic findings in adult with eosinophilic esophagitis. Gastrointest Endosc Clin N Am. 2028;28(1)35-45. doi:10.106/j.giec.2017.08.001
- Schoepfer AM, Safroneeva E, Bussmann C, et al. Delay in diagnosis of eosinophilic esophagitis increases risk for stricture formation in a time-dependent manner. Gastroenterology. 2013.145(6):1230-1236.e1-2. doi:10.1053/j.gastro.2013.08.015
- Chang NC, Thakkar KP, Ketchem CJ, et al. A gap in care leads to progression of fibrosis in eosinophilic esophagitis patients. Clin Gastroenterol Hepatol. 2022;20(8):1701-1708.e2. doi:10.106/j.cgh.2021.10.028
UNCONTROLLED EoE LEADS TO LONG-TERM DAMAGE, LEAVING CHILDREN AT RISK
Assess treatment adherence and efficacy regularly to ensure esophageal healing and inactive EoE, reducing long-term complications and the need for future dilations1
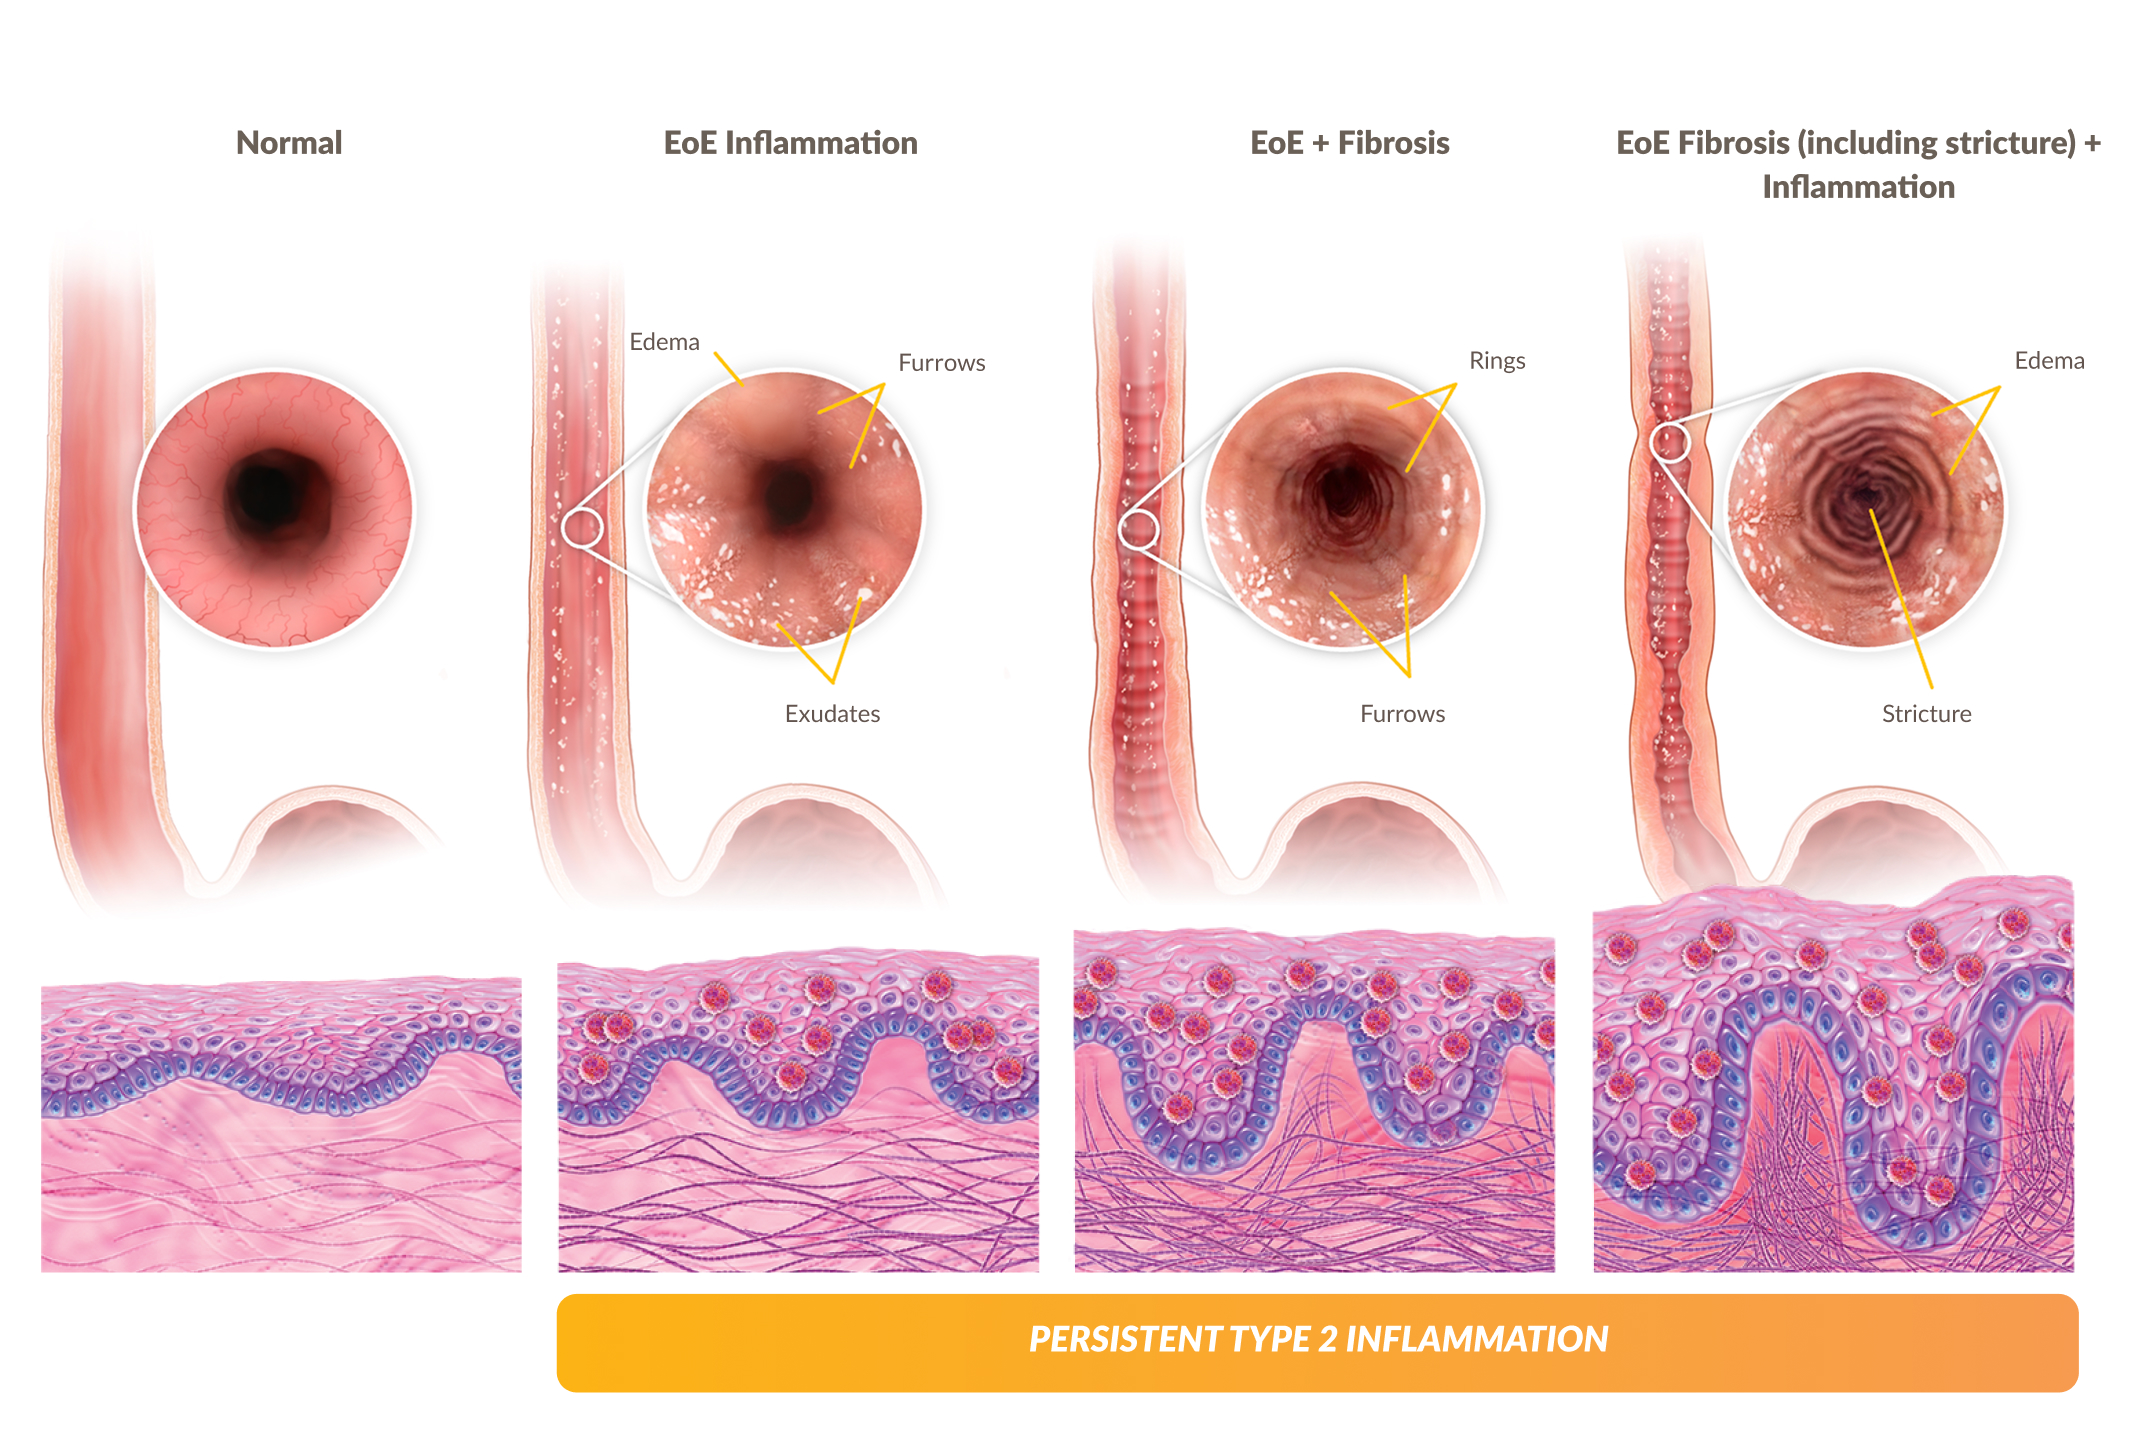


a In this meta-analysis, histologic remission was defined as <5 EOS/HPF, whereas international guidelines and DUPIXENT trials define remission as ≤6 EOS/HPF.
b Retrospective study in 200 adult patients, responders to TCS.
EoE, eosinophilic esophagitis; EOS/HPF, eosinophils per high-power field; PPIs, proton pump inhibitors; TCS, topical corticosteroids.
References:
- Saravino EV, Fassan M, de Bortoli N, et al. Italian EoExpert panel recommendation for disease control, switching criteria, and follow-up in eosinophilic esophagitis from pediatric to adult age. Ther Adv Gastroenterol. 2025;18:17562848251337515. doi:10.1177/17562848251337515
- Lucendo AJ, Gutierrez-Ramirez L, Tejera-Munoz A, et al. Proton pump inhibitors for inducing and maintaining remission in eosinophilic esophagitis: an updated systematic review and meta-analysis. Clin Gastroenterol Hepatol. 2025;23(12):2115-2127.e21. doi:10.1016/j.cgh.2025.01.016
- Schoepfer AM, Safroneeva E, Bussmann C, et al. Delay in diagnosis of eosinophilic esophagitis increases risk for stricture formation in a time-dependent manner. Gastroenterology. 2013.145(6):1230-1236.e1-2. doi:10.1053/j.gastro.2013.08.015
- Chang NC, Thakkar KP, Ketchem CJ, et al. A gap in care leads to progression of fibrosis in eosinophilic esophagitis patients. Clin Gastroenterol Hepatol. 2022;20(8):1701-1708.e2. doi:10.106/j.cgh.2021.10.028
UNCONTROLLED EoE LEADS TO LONG-TERM DAMAGE, LEAVING ADULTS AND ADOLESCENTS AT RISK, EVEN IF THEY SAY THEY ARE FINE
Assess treatment adherence and efficacy regularly to ensure esophageal healing and inactive EoE, reducing long-term complications and the need for future dilations1
a Multicenter study in 269 patients aged ≥17 years.
b Retrospective study in 200 adult patients, responders to TCS.
EoE, eosinophilic esophagitis; TCS, topical corticosteroids.
References:
- Saravino EV, Fassan M, de Bortoli N, et al. Italian EoExpert panel recommendation for disease control, switching criteria, and follow-up in eosinophilic esophagitis from pediatric to adult age. Ther Adv Gastroenterol. 2025;18:17562848251337515. doi:10.1177/17562848251337515
- Safroneeva E, Straumann A, Schoepfer AM. Latest insights on the relationship between symptoms and biologic findings in adult with eosinophilic esophagitis. Gastrointest Endosc Clin N Am. 2028;28(1)35-45. doi:10.106/j.giec.2017.08.001
- Schoepfer AM, Safroneeva E, Bussmann C, et al. Delay in diagnosis of eosinophilic esophagitis increases risk for stricture formation in a time-dependent manner. Gastroenterology. 2013.145(6):1230-1236.e1-2. doi:10.1053/j.gastro.2013.08.015
- Chang NC, Thakkar KP, Ketchem CJ, et al. A gap in care leads to progression of fibrosis in eosinophilic esophagitis patients. Clin Gastroenterol Hepatol. 2022;20(8):1701-1708.e2. doi:10.106/j.cgh.2021.10.028
UNCONTROLLED EoE LEADS TO LONG-TERM DAMAGE, LEAVING CHILDREN AT RISK
Assess treatment adherence and efficacy regularly to ensure esophageal healing and inactive EoE, reducing long-term complications and the need for future dilations1
a In this meta-analysis, histologic remission was defined as <5 EOS/HPF, whereas international guidelines and DUPIXENT trials define remission as ≤6 EOS/HPF.
b Retrospective study in 200 adult patients, responders to TCS.
EoE, eosinophilic esophagitis; EOS/HPF, eosinophils per high-power field; PPIs, proton pump inhibitors; TCS, topical corticosteroids.
References:
- Saravino EV, Fassan M, de Bortoli N, et al. Italian EoExpert panel recommendation for disease control, switching criteria, and follow-up in eosinophilic esophagitis from pediatric to adult age. Ther Adv Gastroenterol. 2025;18:17562848251337515. doi:10.1177/17562848251337515
- Lucendo AJ, Gutierrez-Ramirez L, Tejera-Munoz A, et al. Proton pump inhibitors for inducing and maintaining remission in eosinophilic esophagitis: an updated systematic review and meta-analysis. Clin Gastroenterol Hepatol. 2025;23(12):2115-2127.e21. doi:10.1016/j.cgh.2025.01.016
- Schoepfer AM, Safroneeva E, Bussmann C, et al. Delay in diagnosis of eosinophilic esophagitis increases risk for stricture formation in a time-dependent manner. Gastroenterology. 2013.145(6):1230-1236.e1-2. doi:10.1053/j.gastro.2013.08.015
- Chang NC, Thakkar KP, Ketchem CJ, et al. A gap in care leads to progression of fibrosis in eosinophilic esophagitis patients. Clin Gastroenterol Hepatol. 2022;20(8):1701-1708.e2. doi:10.106/j.cgh.2021.10.028
Adaptive Behaviors
~3 IN 4 EoE PATIENTS USED AT LEAST 1 ADAPTIVE BEHAVIOR DAILY TO COPE WITH SYMPTOMS
88% of patients used at least 1 adaptive behavior per week1,a
| ADAPTIVE BEHAVIORS | QUESTIONS |
| When eating, patient may compensate by2,3: | |
| I = Imbibing fluids with meals | When you eat, do you need a drink to help swallow? How much sauce or condiments do you use? |
| M = Modifying foods | Do you cut your food into smaller pieces than others when you eat? |
| P = Prolonging meal times | Are you typically the last one to finish a meal? |
| A = Avoiding hard texture foods | Do you avoid certain foods (eg. chicken, steak, rice, bread)? |
| C = Chewing excessively | Do you notice that you have to chew more or longer than others when you eat? Do others notice it? |
| T = Turning away tablets/pills | Do you avoid taking tablets or pills? |
| S = Social impairment | How often do you go out to eat? Do you ever make excuses to avoid eating in public? |

|
IDENTIFY ADAPTIVE BEHAVIORS: THEY ARE A SIGN TO FURTHER ASSESS
|
a Based on a retrospective analysis from 2 US databases (n=234).
EoE, eosinophilic esophagitis.
References:
- Chehade M, Pandit-Abid N, Raphael BP, et al. Cross-sectional real-world survey of adult patients with eosinophilic oesophagitis: symptom burden and adaptive behaviors. Presented at: European Academy of Allergy and Clinical Immunology (EAACI 2025), June 13-16, Glasgow, United Kingdom.
- Hirano I, Furuta GT. Approaches and challenges to management of pediatric and adult patients with eosinophilic esophagitis. Gastroenterology. 2020;158(4):840-851. doi:10.1053/j.gastro.2019.09.052
- Larsson H, Strobel MJ, Perez-Guagnelli E. Emotional journey of patients with eosinophilic esophagitis. Adv Ther. 2023;40(12):5254-5270. doi:10.1007/s12325-023-02678-9
UNCOVER ADAPTIVE BEHAVIORS CHILDREN USE TO COPE
Eating behaviors in pediatric patients with EoE evolve with age, making it challenging for providers to unmask them1
| VARIABLES | INFANTS OR TODDLERS | GRADE SCHOOL |
| Duration of
meals |
|
|
| Coping
behaviors |
|
|
| Food selection |
|
|

|
IDENTIFY ADAPTIVE BEHAVIORS: THEY ARE A SIGN TO FURTHER ASSESS ENDOSCOPY AND HISTOLOGY1 |
EoE, eosinophilic esophagitis.
Reference:
- Hirano I, Furuta GT. Approaches and challenges to management of pediatric and adult patients with eosinophilic esophagitis. Gastroenterology. 2020;158(4):840-851. doi:10.1053/j.gastro.2019.09.052
~3 IN 4 EoE PATIENTS USED AT LEAST 1 ADAPTIVE BEHAVIOR DAILY TO COPE WITH SYMPTOMS
88% of patients used at least 1 adaptive behavior per week1,a
| ADAPTIVE BEHAVIORS | QUESTIONS |
| When eating, patient may compensate by2,3: | |
| I = Imbibing fluids with meals | When you eat, do you need a drink to help swallow? How much sauce or condiments do you use? |
| M = Modifying foods | Do you cut your food into smaller pieces than others when you eat? |
| P = Prolonging meal times | Are you typically the last one to finish a meal? |
| A = Avoiding hard texture foods | Do you avoid certain foods (eg. chicken, steak, rice, bread)? |
| C = Chewing excessively | Do you notice that you have to chew more or longer than others when you eat? Do others notice it? |
| T = Turning away tablets/pills | Do you avoid taking tablets or pills? |
| S = Social impairment | How often do you go out to eat? Do you ever make excuses to avoid eating in public? |
|
IDENTIFY ADAPTIVE BEHAVIORS: THEY ARE A SIGN TO FURTHER ASSESS
|
a Based on a retrospective analysis from 2 US databases (n=234).
EoE, eosinophilic esophagitis.
References:
- Chehade M, Pandit-Abid N, Raphael BP, et al. Cross-sectional real-world survey of adult patients with eosinophilic oesophagitis: symptom burden and adaptive behaviors. Presented at: European Academy of Allergy and Clinical Immunology (EAACI 2025), June 13-16, Glasgow, United Kingdom.
- Hirano I, Furuta GT. Approaches and challenges to management of pediatric and adult patients with eosinophilic esophagitis. Gastroenterology. 2020;158(4):840-851. doi:10.1053/j.gastro.2019.09.052
- Larsson H, Strobel MJ, Perez-Guagnelli E. Emotional journey of patients with eosinophilic esophagitis. Adv Ther. 2023;40(12):5254-5270. doi:10.1007/s12325-023-02678-9
UNCOVER ADAPTIVE BEHAVIORS CHILDREN USE TO COPE
Eating behaviors in pediatric patients with EoE evolve with age, making it challenging for providers to unmask them1
| VARIABLES | INFANTS OR TODDLERS | GRADE SCHOOL |
| Duration of
meals |
|
|
| Coping
behaviors |
|
|
| Food selection |
|
|
|
IDENTIFY ADAPTIVE BEHAVIORS: THEY ARE A SIGN TO FURTHER ASSESS ENDOSCOPY AND HISTOLOGY1 |
EoE, eosinophilic esophagitis.
Reference:
- Hirano I, Furuta GT. Approaches and challenges to management of pediatric and adult patients with eosinophilic esophagitis. Gastroenterology. 2020;158(4):840-851. doi:10.1053/j.gastro.2019.09.052
Control
MANY ADULT PATIENTS WITH EoE SUFFER FROM INADEQUATE DISEASE CONTROL WITH PPIs, TCS, AND ELIMINATION DIETS
Achieving control is a key treatment goal in EoE
FAILURE TO ACHIEVE HISTOLOGIC RESPONSE/REMISSION WITH PPIs/TCS/ELIMINATION DIETS
- Only half of patients achieved histologic response (<15 EOS/HPF) across 4 EU countries (DE, IT, SP, UK) during the first 5 years of EoE diagnosis1
- ~63% of patients on PPIs failed to achieve histologic remission (medical follow-up of 4 months)2
HISTOLOGIC RELAPSE AND SYMPTOM RECURRENCE ON PPIs/TCS
- In ~1 in 3 patients, PPIs failed to maintain histologic response (median follow-up of 11.7 months)2
- 61% of patients on TCS showed histological relapse despite continuous treatment (median follow-up of 4-12 months)3,a
- 78% of patients showed histological relapse within 1 year after stopping treatment4,b
- ~57% of patients showed symptom recurrence after stopping TCS (median 8 months)4,c
MANY PATIENTS ON PPIs OR TCS MAY BE UNCONTROLLED, EVEN IF THEY SAY THEY ARE FINE

|
PATIENTS ON TCS CONTINUED TO PROGRESS TO STRICTURE FORMATION WITHIN A 3-YEAR PERIOD. STRICTURE FORMATION INCREASES THE RISK OF FOOD IMPACTION AND THE REQUIREMENT FOR DILATION5-7 |
a Retrospective study of 55 adults with EoE with initial response to TCS, 33 of whom had ≥2 follow-up endoscopies.
b Study in 58 patients with histologic response (<15 EOS/HPF) to TCS who discontinued treatment. 33 of them had symptom recurrence within 1 year after stopping treatment, of which 78% had histologic relapse (≥15 EOS/HPF).
c Study in 58 patients with histologic response (<15 EOS/HPF) to TCS who discontinued treatment. 57% had symptom recurrence after a median of 244 days (8 months).
EoE, eosinophilic esophagitis; EOS/HPF, eosinophils per high-power field; PPIs, proton pump inhibitors; TCS, topical corticosteroids.
References:
- von Arnim U, Zerbib F, Radwan A, et al. Treatment patterns and disease progression among patients with eosinophilic oesophagitis in Europe: a real-world study. Poster PP0085 presented at United European Gastroenterology-2024 (UEGW-2024), October 12-15, Vienna (Messe Wien) Austria
- Lucendo AJ, Gutierrez-Ramirez L, Tejera-Munoz A, et al. Proton pump inhibitors for inducing and maintaining remission in eosinophilic esophagitis: an updated systemic review and meta analysis. Clin Gastroenterol Hepatol. 2025;23(12):2115-2127.e21. doi:10.1015/j.cgh.2025.01.016
- Eluri S, Runge TM, Hansen J, et al. Diminishing effectiveness of long-term maintenance topical steroid therapy in PPI non-responsive eosinophilic esophagitis. Clin Transl Gastroenterol. 2017;8(6):e97. doi:10.1038/ctg.2017.27
- Dellon ES, Gupta SK. Clin Gastroenterol Hepatol. 2019:17(11)2149-2160. doi:10.1016/j.cgh.2019.01.030
- Hirano I, Pandolfino JR, Boeckxstaens GE. Functional lumen imaging probe for the management of esophageal disorders: expert review from clinical practice updates committee of the AGA Institute. Clin Gastroenterol Hepatol. 2017;15(3):325-334. doi:10.1018/j.cgh.2016.10.022
- Nicodeme F, Hirano I, Chen J, et al. Esophageal distensibility as a measure of disease severity in patients with eosinophilic esophagitis. Clin Gastroenterol Hepatol. 2013;11(9):1101-1107. c1.doi:1016/j.cgh.2013.03.020
- Greuter T, Godat A, Ringel A, et al. Effectiveness and safety of high- vs low-dose swallowed topical steroids for maintenance treatment of eosinophilic esophagitis: a multicenter observational study. Clin Gastroenterol Hepatol. 2021;19(12):2514-2523. doi:10.1016/j.cgh.2020.08.27
MANY CHILDREN WITH EoE ARE LEFT UNCONTROLLED WITH PPIs, TCS, AND ELIMINATION DIETS
Achieving control is a key treatment goal in EoE
FAILURE TO ACHIEVE HISTOLOGIC REMISSION ON PPIs
- ~69% of children on PPIs failed to achieve histologic remission1,a
HISTOLOGIC RELAPSE AND SYMPTOM RECURRENCE ON PPIs/TCS
- Up to 54% of children can achieve remission with PPIs, but ~30% relapse if high-dose PPIs are reduced2
- 27% of children failed to maintain remission with TCS at 3 months3
SAFETY CONCERNS WITH PPIs/TCS
- Although generally safe, PPIs raise concerns about the potential negative effects of PPIs on the microbiomes of children2,3
- TCS use is associated with candidiasis and may lead to adrenal suppression2,4
- Coexisting conditions such as asthma, AR, and AD in children may require long-term CS cumulative dose, which may impact their growth4
MANY PATIENTS MAY NOT ACHIEVE DISEASE CONTROL WITH PPIs AND TCS

|
EFFECTIVE EoE TREATMENT IS IMPORTANT TO PREVENT ESOPHAGEAL REMODELING AND STRICTURE FORMATION5 |
a Data from a meta-analysis of 8 studies including 806 patients <18 years of age.
AD, atopic dermatitis; AR, allergic rhinitis; CS, corticosteroids; EoE, eosinophilic esophagitis; PPIs, proton pump inhibitors; TCS, topical corticosteroids.
References:
- Lucendo AJ, Gutierez-Ramirez L, Tejera-Munoz A, et al. Proton pump inhibitors for inducing and maintaining remission in eosinophilic esophagitis: an updated systemic review and meta-analysis. Clin Gastroenterol Hepatol. 2025;23(12):2115-2127.e21. doi:10.1016/j.cgh.2025.01.016
- Chehade M, Hiremath GS, Zevit N, et al. Disease burden and spectrum of symptoms that impact quality of life in pediatric patients with eosinophilic esophagitis. Gastro Hep Adv. 2024;3(8):1054-1068. doi:10.1016/j.gastha.2024.08.009
- Oliva S, Arrigo S, Bramuzzo M, et al. Eosinophilic esophagitis in children and adolescents: a clinical practice guideline. Ital J Pediatr. 2025;51(1):242. doi:10.1186/s13052-025-02056-x
- Chehade M, Katzka DA, Nager S. Thomas RB, Tilton ST. Medical Research Group. A real-world study of cumulative steroid burden among patients with eosinophilic esophagitis in the United States. Clin Gastroenterol Hepatol. 2025;23(9):1665-1667.e3. doi:10.1016/f.cgh.2025.01.030
- Amil-Dias J, Oliva S, Papadopoulou A, et al. Diagnosis and management of eosinophilic esophagitis in children: an update from the European Society for Paediatric Gastroenterology, Hepatology and Nutrition (ESPGHAN). J Pediatr Gastroenterol Nutr. 2024;79(2):394-437. doi:10.1002/jpn.3.12188
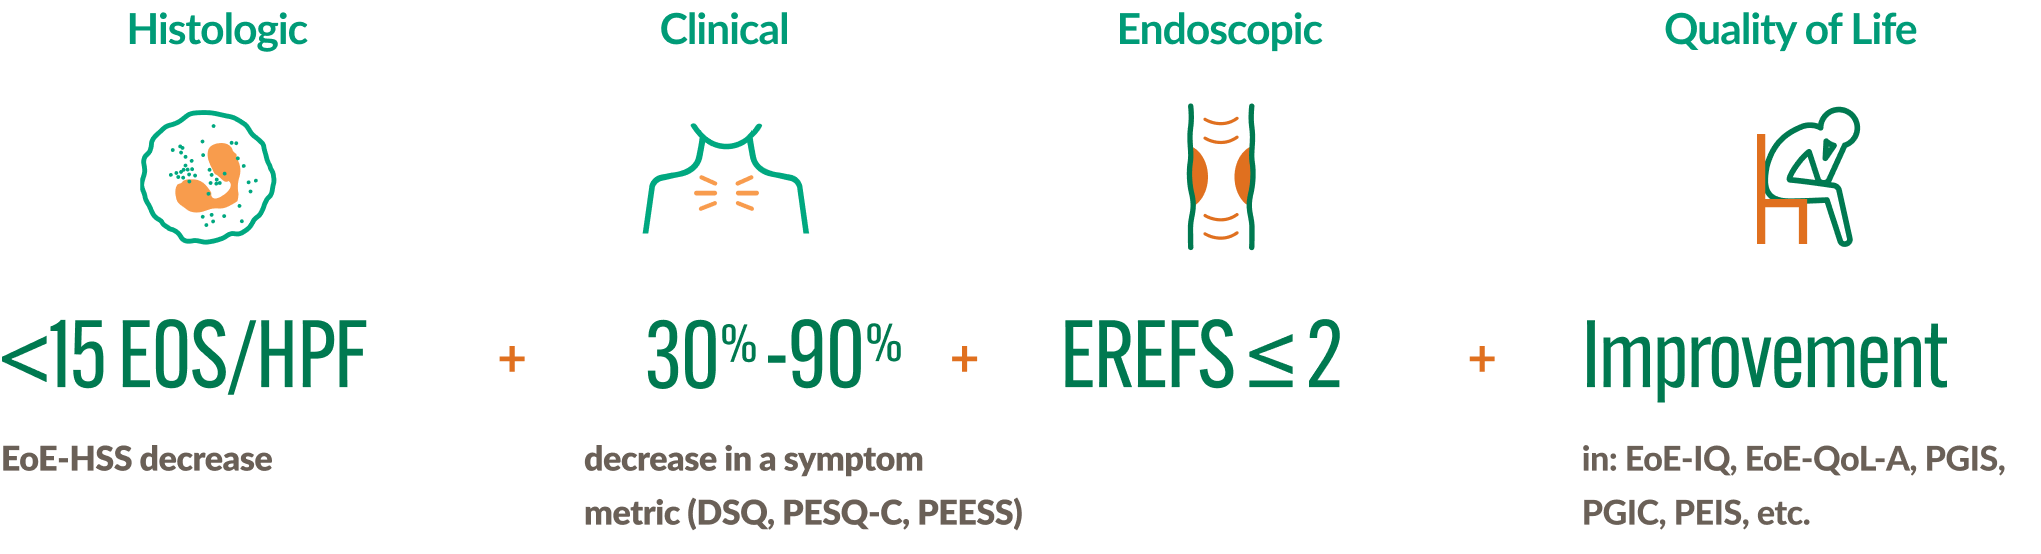
WE CAN DO MORE THAN FINE—PATIENTS WITH EoE NEED A TREATMENT APPROACH THAT HELPS THEM ACHIEVE FULL DISEASE CONTROL
High EoE-associated emotional and psychological burdens and perceived stigma contribute to poor HRQoL1-3
|
FAILURE IN ANY DOMAIN AT THREE MONTHS WARRANTS A SWITCH TO A BIOLOGIC1 |
DSQ, Dysphagia Symptom Questionnaire; EoE-HSS, Eosinophilic Esophagitis Histologic Scoring System; EoE-IQ, EoE Impact Questionnaire; EoE-QoL-A, EoE Quality of Life Questionnaire for Adults; EOS, eosinophils; EREFS, Endoscopic Reference Score; HPF, high-power field; HRQoL, health-related quality of life; PEESS, Pediatric Eosinophilic Esophagitis Symptom Score; PEIS, Pediatric EoE Impact Scale; PESQ-C, Pediatric EoE Signs/Symptoms Questionnaire-Caregiver; PGIC, Patient Global Impression of Change of Dysphagia; PGIS, Patient Global Impression of Severity of Dysphagia.
References:
- Gold BD, Goodwin B, Davis K, et al. Health-related quality of life and perceived stigma in eosinophilic esophagitis: a real-world US, web-based survey. Gastro Hep Adv. 2025;3:1086-1097. doi:10.1016/j.gastha.2024.07.0
- Dellon ES, Gupta SK. A Conceptual Approach to Understanding Treatment Response in Eosinophilic Esophagitis. Clin Gastroenterol Hepatol. 2019;17(11):2149-2160. doi:10.1016/j.cgh.2019.01.030
- Savarino EV, Fassan M, de Bortoli N, et al. Italian EoExpert panel recommendation for disease control, switching criteria, and follow-up in eosinophilic esophagitis from pediatric to adult age. Ther Adv Gastroenterol. 2025;18:17562848251337515. doi:10.1177/1756284251337515
EVEN WHEN THEY SAY THEY ARE FINE, MANY EoE PATIENTS REMAIN UNCONTROLLED
Do you see these uncontrolled EoE patients?
PARTIALLY CONTROLLED ON PPIs/TCS

ASYMPTOMATIC WITH ACTIVE EoE

ADAPTIVE BEHAVIORS

Not real patients.
MANY ADULT PATIENTS WITH EoE SUFFER FROM INADEQUATE DISEASE CONTROL WITH PPIs, TCS, AND ELIMINATION DIETS
Achieving control is a key treatment goal in EoE
FAILURE TO ACHIEVE HISTOLOGIC RESPONSE/REMISSION WITH PPIs/TCS/ELIMINATION DIETS
- Only half of patients achieved histologic response (<15 EOS/HPF) across 4 EU countries (DE, IT, SP, UK) during the first 5 years of EoE diagnosis1
- ~63% of patients on PPIs failed to achieve histologic remission (medical follow-up of 4 months)2
HISTOLOGIC RELAPSE AND SYMPTOM RECURRENCE ON PPIs/TCS
- In ~1 in 3 patients, PPIs failed to maintain histologic response (median follow-up of 11.7 months)2
- 61% of patients on TCS showed histological relapse despite continuous treatment (median follow-up of 4-12 months)3,a
- 78% of patients showed histological relapse within 1 year after stopping treatment4,b
- ~57% of patients showed symptom recurrence after stopping TCS (median 8 months)4,c
MANY PATIENTS ON PPIs OR TCS MAY BE UNCONTROLLED, EVEN IF THEY SAY THEY ARE FINE
|
PATIENTS ON TCS CONTINUED TO PROGRESS TO STRICTURE FORMATION WITHIN A 3-YEAR PERIOD. STRICTURE FORMATION INCREASES THE RISK OF FOOD IMPACTION AND THE REQUIREMENT FOR DILATION5-7 |
a Retrospective study of 55 adults with EoE with initial response to TCS, 33 of whom had ≥2 follow-up endoscopies.
b Study in 58 patients with histologic response (<15 EOS/HPF) to TCS who discontinued treatment. 33 of them had symptom recurrence within 1 year after stopping treatment, of which 78% had histologic relapse (≥15 EOS/HPF).
c Study in 58 patients with histologic response (<15 EOS/HPF) to TCS who discontinued treatment. 57% had symptom recurrence after a median of 244 days (8 months).
EoE, eosinophilic esophagitis; EOS/HPF, eosinophils per high-power field; PPIs, proton pump inhibitors; TCS, topical corticosteroids.
References:
- von Arnim U, Zerbib F, Radwan A, et al. Treatment patterns and disease progression among patients with eosinophilic oesophagitis in Europe: a real-world study. Poster PP0085 presented at United European Gastroenterology-2024 (UEGW-2024), October 12-15, Vienna (Messe Wien) Austria
- Lucendo AJ, Gutierrez-Ramirez L, Tejera-Munoz A, et al. Proton pump inhibitors for inducing and maintaining remission in eosinophilic esophagitis: an updated systemic review and meta analysis. Clin Gastroenterol Hepatol. 2025;23(12):2115-2127.e21. doi:10.1015/j.cgh.2025.01.016
- Eluri S, Runge TM, Hansen J, et al. Diminishing effectiveness of long-term maintenance topical steroid therapy in PPI non-responsive eosinophilic esophagitis. Clin Transl Gastroenterol. 2017;8(6):e97. doi:10.1038/ctg.2017.27
- Dellon ES, Gupta SK. Clin Gastroenterol Hepatol. 2019:17(11)2149-2160. doi:10.1016/j.cgh.2019.01.030
- Hirano I, Pandolfino JR, Boeckxstaens GE. Functional lumen imaging probe for the management of esophageal disorders: expert review from clinical practice updates committee of the AGA Institute. Clin Gastroenterol Hepatol. 2017;15(3):325-334. doi:10.1018/j.cgh.2016.10.022
- Nicodeme F, Hirano I, Chen J, et al. Esophageal distensibility as a measure of disease severity in patients with eosinophilic esophagitis. Clin Gastroenterol Hepatol. 2013;11(9):1101-1107. c1.doi:1016/j.cgh.2013.03.020
- Greuter T, Godat A, Ringel A, et al. Effectiveness and safety of high- vs low-dose swallowed topical steroids for maintenance treatment of eosinophilic esophagitis: a multicenter observational study. Clin Gastroenterol Hepatol. 2021;19(12):2514-2523. doi:10.1016/j.cgh.2020.08.27
MANY CHILDREN WITH EoE ARE LEFT UNCONTROLLED WITH PPIs, TCS, AND ELIMINATION DIETS
Achieving control is a key treatment goal in EoE
FAILURE TO ACHIEVE HISTOLOGIC REMISSION ON PPIs
- ~69% of children on PPIs failed to achieve histologic remission1,a
HISTOLOGIC RELAPSE AND SYMPTOM RECURRENCE ON PPIs/TCS
- Up to 54% of children can achieve remission with PPIs, but ~30% relapse if high-dose PPIs are reduced2
- 27% of children failed to maintain remission with TCS at 3 months3
SAFETY CONCERNS WITH PPIs/TCS
- Although generally safe, PPIs raise concerns about the potential negative effects of PPIs on the microbiomes of children2,3
- TCS use is associated with candidiasis and may lead to adrenal suppression2,4
- Coexisting conditions such as asthma, AR, and AD in children may require long-term CS cumulative dose, which may impact their growth4
MANY PATIENTS MAY NOT ACHIEVE DISEASE CONTROL WITH PPIs AND TCS
|
EFFECTIVE EoE TREATMENT IS IMPORTANT TO PREVENT ESOPHAGEAL REMODELING AND STRICTURE FORMATION5 |
a Data from a meta-analysis of 8 studies including 806 patients <18 years of age.
AD, atopic dermatitis; AR, allergic rhinitis; CS, corticosteroids; EoE, eosinophilic esophagitis; PPIs, proton pump inhibitors; TCS, topical corticosteroids.
References:
- Lucendo AJ, Gutierez-Ramirez L, Tejera-Munoz A, et al. Proton pump inhibitors for inducing and maintaining remission in eosinophilic esophagitis: an updated systemic review and meta-analysis. Clin Gastroenterol Hepatol. 2025;23(12):2115-2127.e21. doi:10.1016/j.cgh.2025.01.016
- Chehade M, Hiremath GS, Zevit N, et al. Disease burden and spectrum of symptoms that impact quality of life in pediatric patients with eosinophilic esophagitis. Gastro Hep Adv. 2024;3(8):1054-1068. doi:10.1016/j.gastha.2024.08.009
- Oliva S, Arrigo S, Bramuzzo M, et al. Eosinophilic esophagitis in children and adolescents: a clinical practice guideline. Ital J Pediatr. 2025;51(1):242. doi:10.1186/s13052-025-02056-x
- Chehade M, Katzka DA, Nager S. Thomas RB, Tilton ST. Medical Research Group. A real-world study of cumulative steroid burden among patients with eosinophilic esophagitis in the United States. Clin Gastroenterol Hepatol. 2025;23(9):1665-1667.e3. doi:10.1016/f.cgh.2025.01.030
- Amil-Dias J, Oliva S, Papadopoulou A, et al. Diagnosis and management of eosinophilic esophagitis in children: an update from the European Society for Paediatric Gastroenterology, Hepatology and Nutrition (ESPGHAN). J Pediatr Gastroenterol Nutr. 2024;79(2):394-437. doi:10.1002/jpn.3.12188
WE CAN DO MORE THAN FINE—PATIENTS WITH EoE NEED A TREATMENT APPROACH THAT HELPS THEM ACHIEVE FULL DISEASE CONTROL
High EoE-associated emotional and psychological burdens and perceived stigma contribute to poor HRQoL1-3
|
FAILURE IN ANY DOMAIN AT THREE MONTHS WARRANTS A SWITCH TO A BIOLOGIC1 |
DSQ, Dysphagia Symptom Questionnaire; EoE-HSS, Eosinophilic Esophagitis Histologic Scoring System; EoE-IQ, EoE Impact Questionnaire; EoE-QoL-A, EoE Quality of Life Questionnaire for Adults; EOS, eosinophils; EREFS, Endoscopic Reference Score; HPF, high-power field; HRQoL, health-related quality of life; PEESS, Pediatric Eosinophilic Esophagitis Symptom Score; PEIS, Pediatric EoE Impact Scale; PESQ-C, Pediatric EoE Signs/Symptoms Questionnaire-Caregiver; PGIC, Patient Global Impression of Change of Dysphagia; PGIS, Patient Global Impression of Severity of Dysphagia.
References:
- Gold BD, Goodwin B, Davis K, et al. Health-related quality of life and perceived stigma in eosinophilic esophagitis: a real-world US, web-based survey. Gastro Hep Adv. 2025;3:1086-1097. doi:10.1016/j.gastha.2024.07.0
- Dellon ES, Gupta SK. A Conceptual Approach to Understanding Treatment Response in Eosinophilic Esophagitis. Clin Gastroenterol Hepatol. 2019;17(11):2149-2160. doi:10.1016/j.cgh.2019.01.030
- Savarino EV, Fassan M, de Bortoli N, et al. Italian EoExpert panel recommendation for disease control, switching criteria, and follow-up in eosinophilic esophagitis from pediatric to adult age. Ther Adv Gastroenterol. 2025;18:17562848251337515. doi:10.1177/1756284251337515
EVEN WHEN THEY SAY THEY ARE FINE, MANY EoE PATIENTS REMAIN UNCONTROLLED
Do you see these uncontrolled EoE patients?
PARTIALLY CONTROLLED ON PPIs/TCS
ASYMPTOMATIC WITH ACTIVE EoE
ADAPTIVE BEHAVIORS
Not real patients.
Assessing EoE
MASTERING EoE THROUGH MULTIDIMENSIONAL CARE
Optimizing EoE care through Symptom Control, Observation, and Patho-Evaluation (S.C.O.P.E.)1

EoE-HSS, eosinophilic esophagitis histology scoring system; EOS/HPF, eosinophils per high-power field; EREFS, Endoscopic Reference Score; I.M.P.A.C.T.S., Imbibing fluids with meals, Modifying foods, Prolonging meal times, Avoiding hard texture foods, Chewing excessively, Turning away tablets/pills, Social impairment; PPIs, proton pump inhibitors; TCS, topical corticosteroids.
References:
- Savarino EV, Fassan M, de Bortoli N, et al. Italian EoExpert panel recommendation for disease control, switching criteria, and follow-up in eosinophilic esophagitis from pediatric to adult age. Ther Adv Gastroenterol. 2025;18:17562848251337515. doi:10.1177/1756284251337515
- Hirano I, Furuta GT. Approaches and challenges to management of pediatric and adult patients with eosinophilic esophagitis. Gastroenterology. 2020;158(4):840-851. doi:10.1053/j.gastro.2019.09.052
- de Rooij WE, Evertsz FB, Lei A, Bredenoord AJ. General well-being and coping strategies in adult eosinophilic esophagitis patients. J Neurogastroenterol Motil. 2022;28(3):390-400. doi:10.5056/jnm21143
- Muir AB, Brown-Whitehorn T, Godwin B, Cianferoni A. Eosinophilic esophagitis: early diagnosis is the key. Clin Exp Gastroenterol. 2019;12:391-399. doi:10.2147/CEG.S175061
- Dellon ES, Gupta SK. A conceptual approach to understanding treatment response in eosinophilic esophagitis. Clin Gastroenterol Hepatol. 2019;17(11):2149-2160. doi:10.1016/j.cgh.2019.01.030
- von Armin U, Zerbib F, Radwan A, et al. Treatment patterns and disease progression among patients with eosinophilic oesophagitis in Europe: A real-world study. Poster PP0085 presented at United European Gastroenterology-2024 (UEGW-2024), October 12-15, Vienna (Messe Wien), Austria.
MASTERING EoE THROUGH MULTIDIMENSIONAL CARE
Optimizing EoE care through Symptom Control, Observation, and Patho-Evaluation (S.C.O.P.E.)1
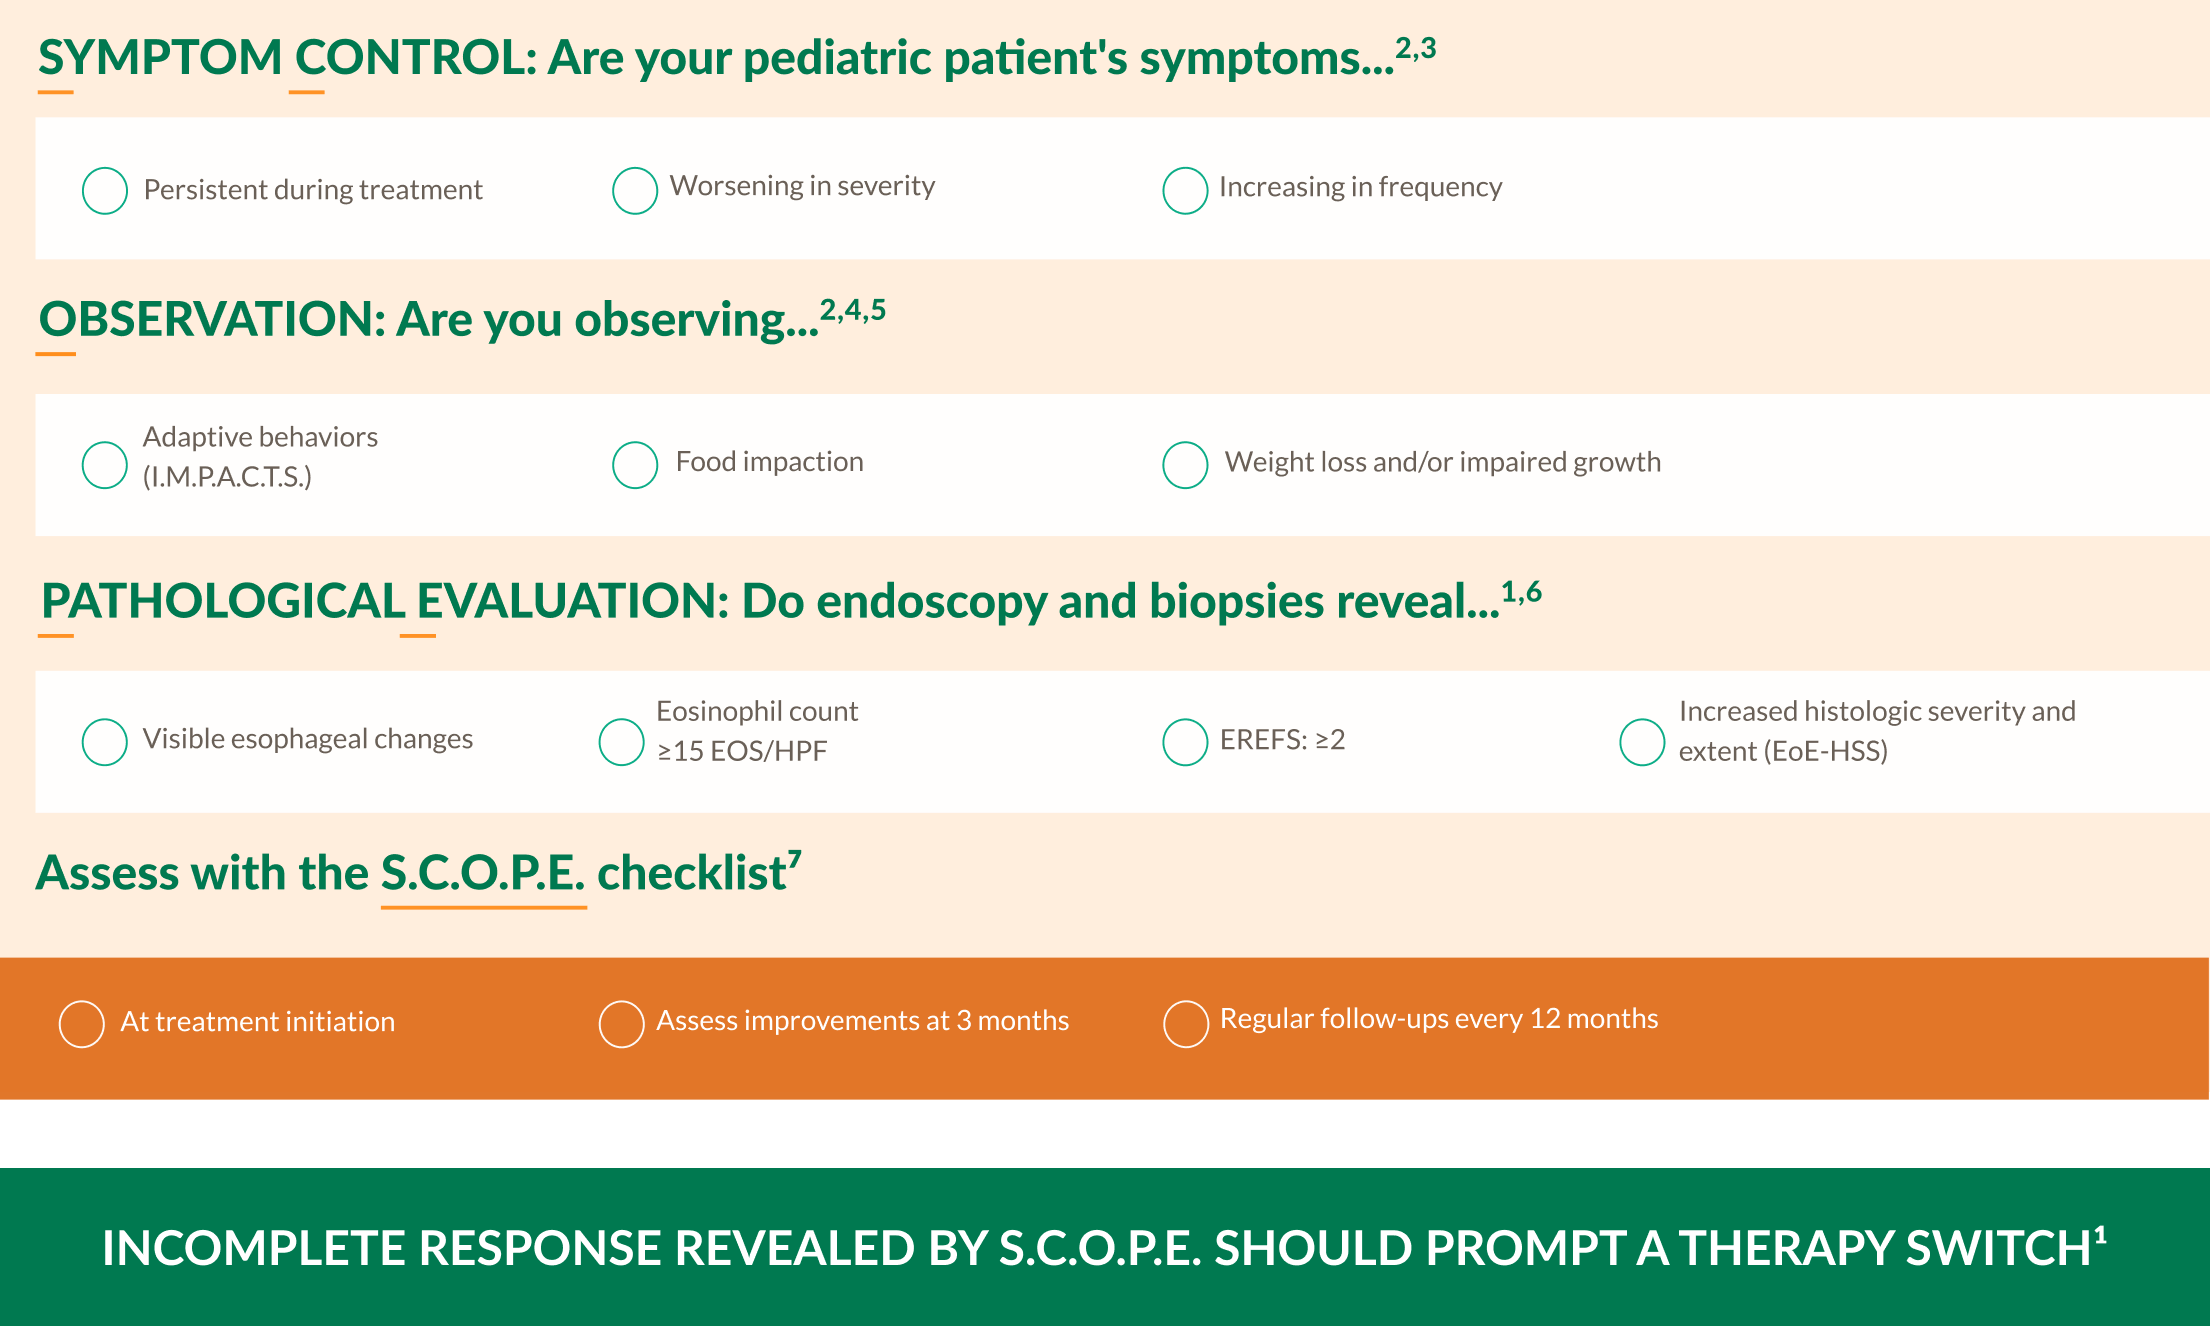
EoE-HSS, eosinophilic esophagitis histology scoring system; EOS/HPF, eosinophils per high-power field; EREFS, Endoscopic Reference Score; I.M.P.A.C.T.S., Imbibing fluids with meals, Modifying foods, Prolonging meal times, Avoiding hard texture foods, Chewing excessively, Turning away tablets/pills, Social impairment.
References:
- Savarino EV, Fassan M, de Bortoli N, et al. Italian EoExpert panel recommendation for disease control, switching criteria, and follow-up in eosinophilic esophagitis from pediatric to adult age. Ther Adv Gastroenterol. 2025;18:17562848251337515. doi:10.1177/1756284251337515
- Hirano I, Furuta GT. Approaches and challenges to management of pediatric and adult patients with eosinophilic esophagitis. Gastroenterology. 2020;158(4):840-851. doi:10.1053/j.gastro.2019.09.052
- de Rooij WE, Evertsz FB, Lei A, Bredenoord AJ. General well-being and coping strategies in adult eosinophilic esophagitis patients. J Neurogastroenterol Motil. 2022;28(3):390-400. doi:10.5056/jnm21143
- Wechsler JB, Bolton SM, Amsden K, Wershil BK, Hirano I, Kagalwalla AF. Eosinophilic esophagitis reference score accurately identifies disease activity and treatment effects in children. Clin Gastroenterol Hepatol. 2018;16(7)1056-1063. doi:10.1016/j.cgh.2017.12.019
- Muir AB, Brown-Whitehorn T, Godwin B, Cianferoni A. Eosinophilic esophagitis: early diagnosis is the key. Clin Exp Gastroenterol. 2019;12:391-399. doi:10.2147/CEG.S175061
- Dellon ES, Gupta SK. Clin Gastroenterol Hepatol. 2019;17(11):2149-2160. doi:10.1016/j.cgh.2019.01.030
- von Armin U, Zerbib F, Radwan A, et al. Treatment patterns and disease progression among patients with eosinophilic oesophagitis in Europe: A real-world study. Poster PP0085 presented at United European Gastroenterology-2024 (UEGW-2024), October 12-15, Vienna (Messe Wien), Austria.
HOW TO DO MORE: GO BEYOND SYMPTOMS WITH HISTOLOGY AND ENDOSCOPY
Blood biomarkers are still lacking in clinical practice or are inaccurate (blood eosinophil level does not correlate with esophageal eosinophil count or disease activity)1,2

|
ONLY ENDOSCOPY + BIOPSY CAN REVEAL HIDDEN PROGRESSION4 |
COLLABORATION MATTERS BETWEEN GASTROENTEROLOGISTS AND PATHOLOGISTS
Making an accurate diagnosis with a complete pathology report (including EoE-HSS when possible) may provide new insights on EoE pathophysiology and on the progression of the disease5

|
EoE WARRANTS HOLISTIC MANAGEMENT5 |
EoE-HSS, eosinophilic esophagitis histology scoring system; PEC, peak eosinophil count.
References:
- Noble SL, Tyrrell R, Mules TC, Inns S. Non-invasive biomarkers to diagnose and monitor eosinophilic esophagitis: a systemic review. Front Med (Lausanne). 2025;12:1607306. doi:10.3389/fmed.2025.1607306
- Chehade M, Falk GW, Aceves S, et al. Examining the role of type 2 inflammation in eosinophilic esophagitis. Gastro Hep Adv. 2022;1(5):720-732. doi:10.1016/j.gastha.2022.05.004
- Lucendo AJ, Molina-Infante J, Arias A, et al. Guidelines on eosinophilic esophagitis: evidence-based statements and recommendations for diagnosis and management in children and adults. United European Gastroenterol J. 2017;5(3):335-358. doi:10.1177/2050640616689525
- Aceves SS, Alexander JA, Baron TH, et al. Endoscopic approach to eosinophilic esophagitis: American Society for Gastrointestinal Endoscopy Consensus Conference. Gastrointest Endosc. 2022;96(4):576-592.e1. doi:10.1016/j.gie.2022.05.013
- Salvatore S. Eosinophilic esophagitis: when pathologists make the difference. J Pediatr (Rio J). 2022;98(1):1-3. doi:10.1016/j.ped.2021.08.001
MASTERING EoE THROUGH MULTIDIMENSIONAL CARE
Optimizing EoE care through Symptom Control, Observation, and Patho-Evaluation (S.C.O.P.E.)1
EoE-HSS, eosinophilic esophagitis histology scoring system; EOS/HPF, eosinophils per high-power field; EREFS, Endoscopic Reference Score; I.M.P.A.C.T.S., Imbibing fluids with meals, Modifying foods, Prolonging meal times, Avoiding hard texture foods, Chewing excessively, Turning away tablets/pills, Social impairment; PPIs, proton pump inhibitors; TCS, topical corticosteroids.
References:
- Savarino EV, Fassan M, de Bortoli N, et al. Italian EoExpert panel recommendation for disease control, switching criteria, and follow-up in eosinophilic esophagitis from pediatric to adult age. Ther Adv Gastroenterol. 2025;18:17562848251337515. doi:10.1177/1756284251337515
- Hirano I, Furuta GT. Approaches and challenges to management of pediatric and adult patients with eosinophilic esophagitis. Gastroenterology. 2020;158(4):840-851. doi:10.1053/j.gastro.2019.09.052
- de Rooij WE, Evertsz FB, Lei A, Bredenoord AJ. General well-being and coping strategies in adult eosinophilic esophagitis patients. J Neurogastroenterol Motil. 2022;28(3):390-400. doi:10.5056/jnm21143
- Muir AB, Brown-Whitehorn T, Godwin B, Cianferoni A. Eosinophilic esophagitis: early diagnosis is the key. Clin Exp Gastroenterol. 2019;12:391-399. doi:10.2147/CEG.S175061
- Dellon ES, Gupta SK. A conceptual approach to understanding treatment response in eosinophilic esophagitis. Clin Gastroenterol Hepatol. 2019;17(11):2149-2160. doi:10.1016/j.cgh.2019.01.030
- von Armin U, Zerbib F, Radwan A, et al. Treatment patterns and disease progression among patients with eosinophilic oesophagitis in Europe: A real-world study. Poster PP0085 presented at United European Gastroenterology-2024 (UEGW-2024), October 12-15, Vienna (Messe Wien), Austria.
MASTERING EoE THROUGH MULTIDIMENSIONAL CARE
Optimizing EoE care through Symptom Control, Observation, and Patho-Evaluation (S.C.O.P.E.)1
EoE-HSS, eosinophilic esophagitis histology scoring system; EOS/HPF, eosinophils per high-power field; EREFS, Endoscopic Reference Score; I.M.P.A.C.T.S., Imbibing fluids with meals, Modifying foods, Prolonging meal times, Avoiding hard texture foods, Chewing excessively, Turning away tablets/pills, Social impairment.
References:
- Savarino EV, Fassan M, de Bortoli N, et al. Italian EoExpert panel recommendation for disease control, switching criteria, and follow-up in eosinophilic esophagitis from pediatric to adult age. Ther Adv Gastroenterol. 2025;18:17562848251337515. doi:10.1177/1756284251337515
- Hirano I, Furuta GT. Approaches and challenges to management of pediatric and adult patients with eosinophilic esophagitis. Gastroenterology. 2020;158(4):840-851. doi:10.1053/j.gastro.2019.09.052
- de Rooij WE, Evertsz FB, Lei A, Bredenoord AJ. General well-being and coping strategies in adult eosinophilic esophagitis patients. J Neurogastroenterol Motil. 2022;28(3):390-400. doi:10.5056/jnm21143
- Wechsler JB, Bolton SM, Amsden K, Wershil BK, Hirano I, Kagalwalla AF. Eosinophilic esophagitis reference score accurately identifies disease activity and treatment effects in children. Clin Gastroenterol Hepatol. 2018;16(7)1056-1063. doi:10.1016/j.cgh.2017.12.019
- Muir AB, Brown-Whitehorn T, Godwin B, Cianferoni A. Eosinophilic esophagitis: early diagnosis is the key. Clin Exp Gastroenterol. 2019;12:391-399. doi:10.2147/CEG.S175061
- Dellon ES, Gupta SK. Clin Gastroenterol Hepatol. 2019;17(11):2149-2160. doi:10.1016/j.cgh.2019.01.030
- von Armin U, Zerbib F, Radwan A, et al. Treatment patterns and disease progression among patients with eosinophilic oesophagitis in Europe: A real-world study. Poster PP0085 presented at United European Gastroenterology-2024 (UEGW-2024), October 12-15, Vienna (Messe Wien), Austria.
HOW TO DO MORE: GO BEYOND SYMPTOMS WITH HISTOLOGY AND ENDOSCOPY
Blood biomarkers are still lacking in clinical practice or are inaccurate (blood eosinophil level does not correlate with esophageal eosinophil count or disease activity)1,2
|
ONLY ENDOSCOPY + BIOPSY CAN REVEAL HIDDEN PROGRESSION4 |
COLLABORATION MATTERS BETWEEN GASTROENTEROLOGISTS AND PATHOLOGISTS
Making an accurate diagnosis with a complete pathology report (including EoE-HSS when possible) may provide new insights on EoE pathophysiology and on the progression of the disease5
|
EoE WARRANTS HOLISTIC MANAGEMENT5 |
EoE-HSS, eosinophilic esophagitis histology scoring system; PEC, peak eosinophil count.
References:
- Noble SL, Tyrrell R, Mules TC, Inns S. Non-invasive biomarkers to diagnose and monitor eosinophilic esophagitis: a systemic review. Front Med (Lausanne). 2025;12:1607306. doi:10.3389/fmed.2025.1607306
- Chehade M, Falk GW, Aceves S, et al. Examining the role of type 2 inflammation in eosinophilic esophagitis. Gastro Hep Adv. 2022;1(5):720-732. doi:10.1016/j.gastha.2022.05.004
- Lucendo AJ, Molina-Infante J, Arias A, et al. Guidelines on eosinophilic esophagitis: evidence-based statements and recommendations for diagnosis and management in children and adults. United European Gastroenterol J. 2017;5(3):335-358. doi:10.1177/2050640616689525
- Aceves SS, Alexander JA, Baron TH, et al. Endoscopic approach to eosinophilic esophagitis: American Society for Gastrointestinal Endoscopy Consensus Conference. Gastrointest Endosc. 2022;96(4):576-592.e1. doi:10.1016/j.gie.2022.05.013
- Salvatore S. Eosinophilic esophagitis: when pathologists make the difference. J Pediatr (Rio J). 2022;98(1):1-3. doi:10.1016/j.ped.2021.08.001