
Pediatric |
With ELOCTATE individualized prophylaxis, children <12 experienced a decrease in overall ABR over 4 years of clinical data1-5†
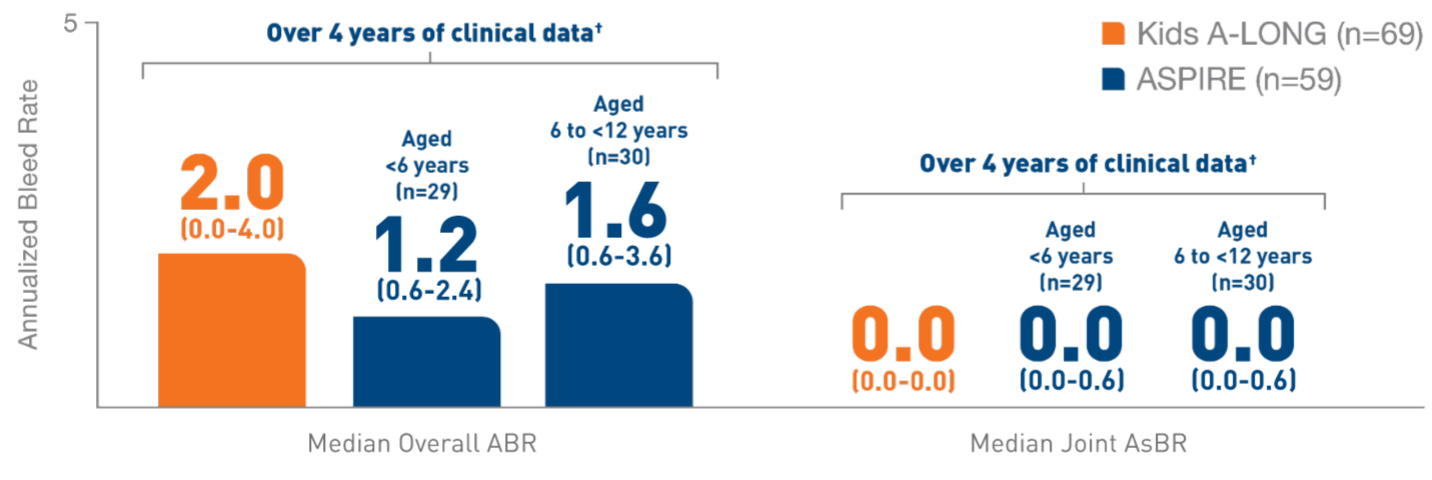
In the individualized prophylaxis arm, additional median annualized bleed rates were:
- AsBR: 0.0 (0.0–0.0) [<6 years old], 0.0 (0.0-0.0) [6 to <12 years old] in Kids A-LONG; 0.6 (0.0-0.9) [<6 years old], 0.3 (0.0–0.9) [6 to <12 years old] in ASPIRE2,3
- Traumatic ABR: 0.0 (0.0–2.01) [<6 years old], 0.0 (0.0–2.12) [6–<12 years old] in Kids A-LONG; 0.4 (0.0–0.9) [<6 years old], 1.0 (0.0–2.1) [6 to <12 years old] in ASPIRE3,4
- Joint ABR: 0.0 (0.0–1.9) [<6 years old], 0.0 (0.0-2.0) [6 to <12 years old] in Kids A-LONG; 0.6 (0.0–1.3) [<6 years old], 0.7 (0.0–1.7) [6 to <12 years old] in ASPIRE2,3
In the Kids A-LONG study, individualized prophylaxis regimen: 25 IU/kg and 50 IU/kg of ELOCTATE on the first and fourth days of the week, respectively. Adjustments in dose (25 to 80 IU/kg) and interval (every 2 days or longer) were allowed based on a subject’s available PK data and observed bleeding pattern.4
In the ASPIRE study, the individualized prophylaxis regimen was 25 to 65 IU/kg every 3 to 5 days, or twice weekly (20 to 65 IU/kg on Day 1, 40 to 65 IU/kg on Day 4). In subjects <12 years of age, dose adjustments were made up to a maximum of 80 IU/kg up to every 2 days, if necessary.3
Nearly 100% of target joints‡ were resolved with ELOCTATE prophylaxis6§
- In 111 adult and adolescent patients taking ELOCTATE prophylaxis, 234 out of 235 target joints were resolved
- In 13 pediatric patients taking ELOCTATE prophylaxis, 9 out of 9 target joints were resolved
* ELOCTATE has been proven to help patients prevent bleeding episodes using a prophylaxis regimen.2
† The median treatment duration from the beginning of Kids A-LONG to the end of ASPIRE was 3.5 years (range: 0 to 4.4 years).5
‡ A target joint is defined as a major joint with ≥3 bleeding episodes in a consecutive 6-month period. Target joint resolution is defined as ≤2 spontaneous bleeds in a 12-month period.6
§ Data based on a post-hoc analysis of the ASPIRE extension trial presented at EAHAD 2019. 54 adult and adolescent patients, and 56 pediatric patients, had no target joints at baseline when enrolled in A-LONG and Kids A-LONG, respectively.4,6,8
ABR=annualized bleed rate; AsBR=annualized spontaneous bleed rate; PK=pharmacokinetic.

INDICATION
References: 1. Konkle B, et al. Res Prac Thromb Haemost. 2023;7(6):102180. 2. Eloctate Prescribing Information. Bioverativ Therapeutics Inc. Waltham, MA. 3. Nolan B, et al. Haemophilia. 2020;26(suppl 3)494-502. 4. Young G, et al. J Thromb Haemost. 2015;13(6):1-11. 5. Nolan B, et al. Haemophilia. 2020;26(3):494-502. 6. Oldenburg J, et al. Poster presented at: 12th Annual Congress of the European Association for Haemophilia and Allied Disorders; February 2019; Prague, Czech Republic. 7. Konkle B, et al. Poster presented at: 12th Annual Congress of the European Association for Haemophilia and Allied Disorders; February 2019; Prague, Czech Republic. 8. Mahlangu J, et al. Blood. 2014;123(3):317-325. 9. Mahlangu J, et al. Res Prac Thromb Haemost. 2016;116(1):1-8. 10. Nolan B, et al. Poster presented at: 60th American Society of Hematology Annual Meeting & Exposition; December 2018; San Diego, CA.
